
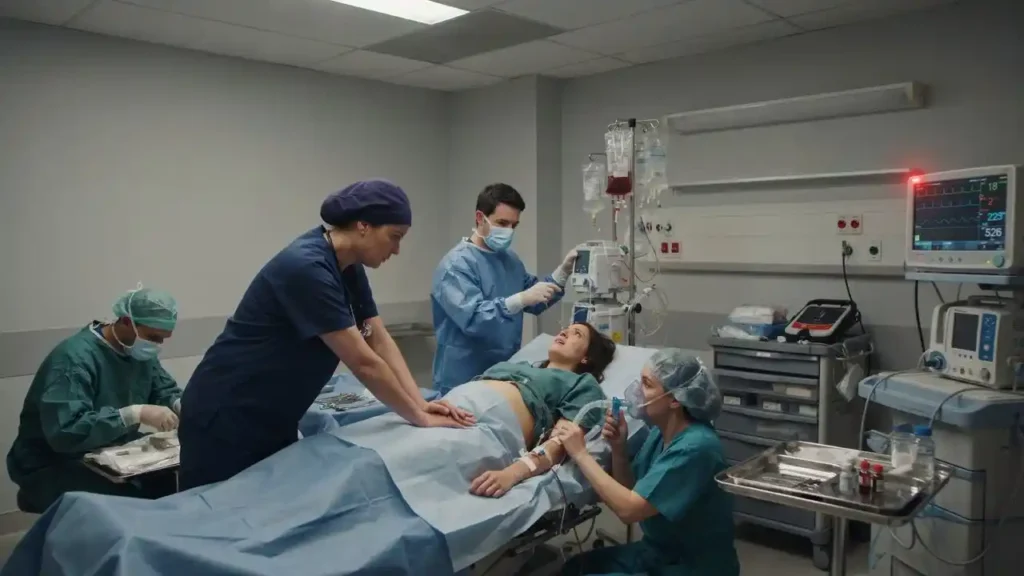
A laboring patient stops breathing without warning. Her blood pressure crashes, her monitor alarms fire at once, and she loses consciousness within seconds. This is the reality of Amniotic Fluid Embolism Nursing: your team gets almost no time to think before acting.
AFE kills up to half of the women who experience it within the first hour, and it strikes patients with zero risk factors just as often as those with known complications. Guessing at the next step costs lives. Knowing the exact signs, the treatment sequence, and your role as first responder is what changes the outcome for both mother and baby.
Amniotic Fluid Embolism (AFE) occurs when amniotic fluid or fetal cells enter the mother’s bloodstream and trigger a sudden, severe reaction. The body responds the way it would to a massive allergic exposure, not a blocked artery. This is why clinicians increasingly call AFE an anaphylactoid syndrome of pregnancy rather than a true embolism.
The reaction causes the lungs and heart to fail almost simultaneously. Blood clotting also breaks down within minutes, leading to uncontrolled bleeding. Every system a nurse monitors during labor can collapse at once.
Amniotic Fluid Embolism in Pregnancy ranks as the second leading cause of maternal death and peripartum cardiac arrest in the United States. It affects less than 1% of pregnancies, yet its outcomes are severe enough that every labor and delivery nurse needs a plan before it happens. Amniotic Fluid Embolism During Labor can appear in a healthy patient with no prior complications and no warning signs on the chart.
This unpredictability is the core problem. Standard risk-factor screening will not catch most cases. Your ability to recognize the early signs at the bedside is often the only warning system available.
Early AFE symptoms mimic ordinary pregnancy discomfort, which is exactly why nurses miss them. Watch for sudden agitation, a feeling of panic the patient cannot explain, chills, nausea, or a cough that appears out of nowhere. Report any of these paired with a subtle drop in oxygen saturation immediately.
As the condition progresses, the picture becomes unmistakable. Look for rapid shallow breathing, a bluish tinge around the lips or fingertips, falling blood pressure, and fetal heart rate abnormalities. Seizures, unresponsiveness, and cardiac arrest can follow within minutes if the team does not intervene.
Amniotic Fluid Embolism Emergency Management follows a specific sequence, and every second matters. Use this order as your mental checklist during a suspected event.
Amniotic Fluid Embolism Nursing Care does not end once the patient stabilizes. Continue frequent neurological checks, since brain injury from oxygen deprivation can appear hours after the initial event. Watch renal function closely, because acute kidney injury is a common complication in survivors.
Document the timeline in detail while it is fresh. Note when symptoms started, every intervention given, and the exact times of delivery and stabilization, since this record matters for both patient safety and legal review. Keep the family informed at every stage and give them direct access to the patient, since clear communication reduces their distress during a frightening event.
A large United States cohort study examined over 14 million deliveries and found AFE in roughly 6 per 100,000 live births, higher than older estimates suggested, according to data compiled by the National Organization for Rare Disorders. The same study found a fail-to-rescue rate of 17% after AFE, compared to an overall maternal mortality rate of 1.7%. That rate climbed past 30% when cardiac arrest, coagulopathy, and shock occurred together.
These numbers point to one thing: intervention speed and coordination determine survival more than any single treatment. A nurse who recognizes the pattern in the first ninety seconds gives the team the head start it needs.
AFE shares symptoms with several other emergencies, which makes fast differentiation critical. Use these one-line distinctions to rule conditions in or out at the bedside.
Reading about Amniotic Fluid Embolism Management is different from practicing the response until it becomes automatic. At Cheap CE For Nurses, our Amniotic Fluid Embolism: Recognizing the Signs course walks through the full emergency sequence, differential diagnosis, and Amniotic Fluid Embolism Treatment protocols in a format built for working nurses. It delivers 3 contact hours toward your Amniotic Fluid Embolism Continuing Education Nursing requirements, and you can complete it entirely online.
This Amniotic Fluid Embolism Nursing Course Online works as a standalone Amniotic Fluid Embolism Nursing CEU credit or as part of a full nursing CE course library if you need multiple renewal hours at once. Check our state CE requirements FAQ if you have questions before you enroll.
AFE gives you minutes, not hours, to act correctly. Review the emergency sequence above until you can recite it without looking, then enroll in the CE course through Cheap CE For Nurses to lock in the 3 contact hours and the muscle memory that saves lives.
Yes. Early signs like sudden agitation, chills, and an unexplained cough often appear minutes before the more severe symptoms. Reporting these changes immediately gives the team a head start on treatment.
No. Current evidence shows survivors can go on to have normal pregnancies afterward, and recurrence rates are not clearly elevated.
Tilting the patient at least 15 degrees relieves pressure on the major blood vessels near the uterus. This simple positioning step improves circulation and reduces fetal distress while the team prepares further treatment.
Waiting until after the crisis to record times and interventions. Details fade fast during a code, so documenting in real time, even in shorthand, protects the accuracy of the record.
This course provides 3 contact hours toward your continuing education nursing requirements, and you receive an instant certificate on completion.